


Who’s Zooming Who?

It began with a U.S. Senate investigation.
A report led by Senator Chuck Grassley examining UnitedHealth Group’s role in Medicare Advantage risk adjustment documents how the current payment structure incentivizes aggressive disease documentation — making patients appear sicker on paper in order to drive higher payment multiples from Medicare.
The central allegation is not subtle: the structure of Medicare Advantage payments rewards coding intensity, not necessarily worse health. UnitedHealth is uniquely poised to run the bully pulpit in this paradigm. They are vertically integrated to acquire providers and data from the womb to the tomb. They not only harnessed their resources to perpetrate billing fraud, they even sell their tools to other Medicare Advantage insurance companies.
But as I worked through the report, something unexpected happened.
A single paragraph about Medicare Part D prescription drug spending forced me to re-examine an assumption I — like most physicians and patients — had never questioned.
The assumption most of us get wrong
Most people believe that when a Medicare beneficiary pays a monthly premium for Medicare Advantage or Part D:
That premium is paid to an insurance company
The insurer then uses that money to pay for care and medications
That assumption is wrong.
In reality, Medicare Advantage and Part D premiums are not paid to insurers at all. Premiums are largely withheld from Social Security benefits, credited to the U.S. Treasury, and administered by CMS, which then pays private plans prospectively based on bids and risk adjustment.²
The Senate report makes this explicit in the Part D section:
“CMS (Centers For Medicare and Medicaid Services) generally provides MA-PDs (Medicare Advantage and Part D plan) and standalone Prescription Drug Plans with a risk-adjusted subsidy that aims to average 74.5 percent of basic benefit costs for all types of beneficiaries.”
This means that Medicare — not insurers — finances the majority of prescription drug spending, with private plans acting as administrators of public funds, not traditional risk-bearing insurers.
Because it changes the question from-
“Is UnitedHealth behaving badly?”
to
“What incentives does the system itself create?”
Why drug pricing became impossible to ignore
The Senate report further explains that Medicare Part D subsidies are adjusted using the RxHCC system, a diagnosis-based model derived from the same conceptual framework as Medicare Advantage risk adjustment. RxHCC stands for Prescription Drug Hierarchical Condition Categories.
What RxHCC Really Means (Plain English)
RxHCC stands for Prescription Drug Hierarchical Condition Categories.
It is Medicare’s diagnosis-based system for adjusting Part D prescription drug payments to private plans.
In simple terms:
Doctors document diagnoses using ICD (International Classification of Diseases) codes
Those diagnoses are grouped into RxHCC categories
Each category increases a patient’s “risk score”
Higher risk scores result in higher Medicare payments to plans
Crucially, RxHCC payment factors are calibrated using gross prescription drug spending — not actual drug acquisition costs or cash prices.
That means if drug prices are inflated today, those inflated prices become the baseline for future Medicare payments.
RxHCC does not just follow illness.
It locks in pricing structures, efficient or not.
For emphasis- RxHCC payment factors are calibrated using gross prescription drug expenditures, not acquisition cost or net prices. Nowhere can I find who or where these prices are generated. It appears this is “proprietary” between CMS and the insurance industry. What the heck??
“For each demographic group, the relative factor for each RxHCC is calculated based on diagnosis information from a base year and gross prescription drug expenditures from the following year.”
In other words:
Whatever price exists at the point of claim submission
Becomes embedded into future federal payments
Medicare does not ask:
What did the drug cost to manufacture?
What did the pharmacy pay to acquire it?
Could the same drug have been dispensed more efficiently?
It simply finances the price that appears on paper.
That is where generic drugs become impossible to ignore.
The generic drug contradiction
Generic medications are:
Off-patent
Widely manufactured usually from multiple sources- commoditized.
Highly competitive
Inexpensive at wholesale
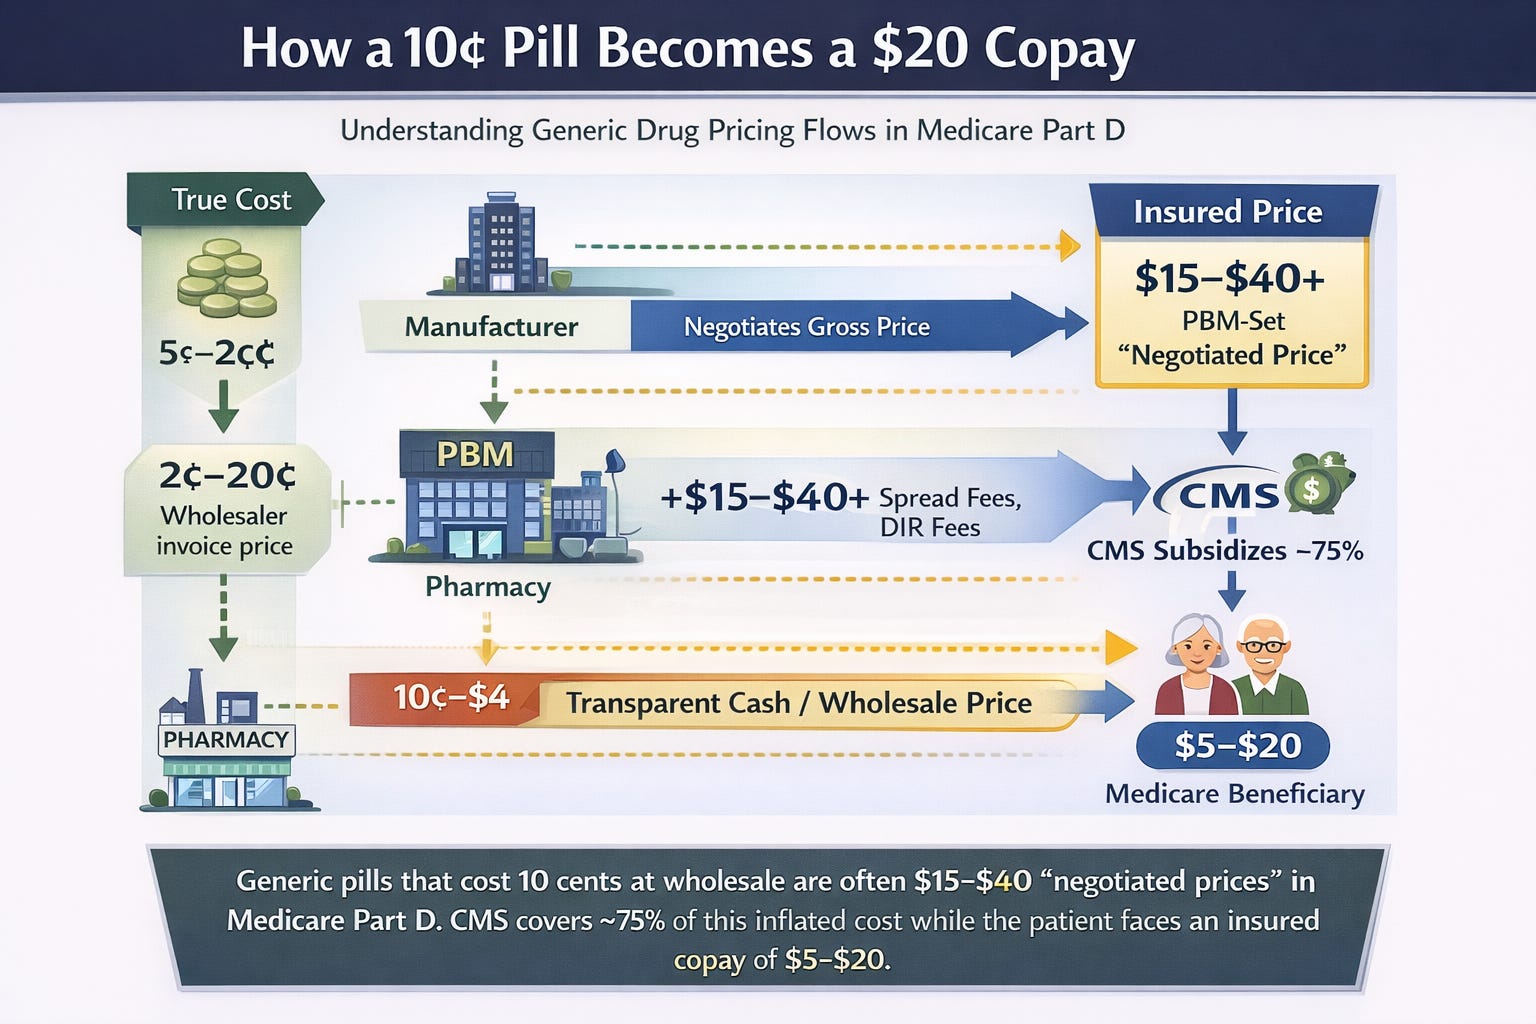
In real clinical practice — including my own — many generics can be purchased directly from wholesalers and dispensed to patients for pennies, nickels and dimes per pill.
Yet when routed through Medicare Part D:
The same drugs are assigned “negotiated prices”
Patients face copays or coinsurance based on those prices
CMS subsidizes roughly three-quarters of the inflated amount
Independent drug-pricing analysts at 46Brooklyn Research have repeatedly shown that this inflation has little to do with drug cost and everything to do with intermediary pricing layers, including Prescription Benefit Managers spread pricing, administrative fees, and opaque contract structures.
Insurance does not lower the price of generics. It raises them.
This is not insurance — it is public finance with private branding
At this point, the pattern becomes clear:
Medicare Advantage inflates payments through documentation incentives
Medicare Part D inflates spending through price opacity
Both are financed primarily by public funds
Both rely on private companies whose revenues rise with higher gross spending, not efficiency
Generic drugs — predictable, low-cost commodities — do not belong in insurance pools.
They are not catastrophic risks.
They are not unpredictable events.
They do not require risk spreading.
They require price transparency and competition. The Medicare Part D Insurance scam totally contradicts this economic dynamic.
The obvious conclusion policymakers avoid
Using real-world dispensing experience, public Senate findings, and transparent pricing analysis from 46Brooklyn, the conclusion is unavoidable:
“Independent analyses by 46Brooklyn Research consistently show that multi-source generics have very low acquisition costs, while insured ‘negotiated prices’ are often an order of magnitude higher due to PBM pricing structures. These dynamics apply across commercial insurance, Medicare Part D, and cash markets.”
Generic prescriptions and Medicare Part D do not belong inside insurance structures.
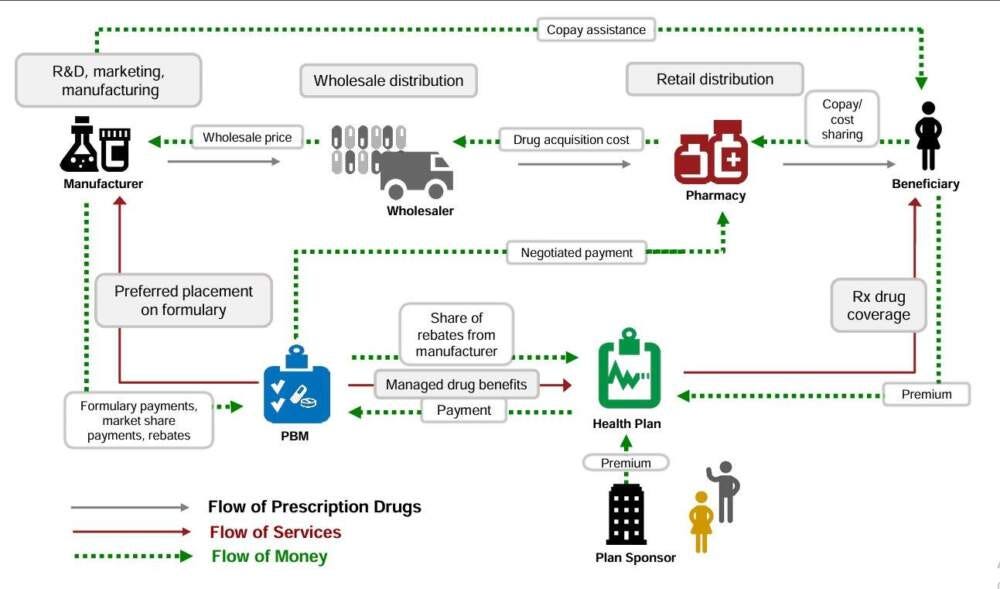
A cost-plus pharmacy model — whether local, regional, or national — would:
Deliver medications at near-acquisition cost
Preserve fair, market-based profit for pharmacies
Improve adherence
Reduce federal spending
Eliminate PBM rent extraction
Restore insurance to its proper role: covering risk, not commodities
The infrastructure already exists.
Physicians and pharmacies already do this.
The only thing missing is policy permission.
What this review really uncovered
The UnitedHealth Senate investigation may have begun with diagnosis coding.
But it exposes something larger:
A Medicare system that no longer distinguishes between:
Risk and routine
Insurance and administration
Cost and price
When insurance stops being insurance, inefficiency is no longer accidental — it is structural.
And generic drugs are the clearest place to start fixing it.

Footnotes
U.S. Senate Judiciary Committee, Majority Staff Report, How UnitedHealth Group Puts the Risk in Medicare Advantage Risk Adjustment (2024).
grassleyunh0112
Centers for Medicare & Medicaid Services, Medicare Prescription Drug Benefit Manual, Ch. 1 (premium collection and payment mechanics).
Senate Judiciary Committee Majority Staff Report, Medicare Part D subsidy discussion.
grassleyunh0112
Senate Judiciary Committee Majority Staff Report, RxHCC calibration methodology.
grassleyunh0112
46Brooklyn Research, multiple analyses of generic pricing, PBM spread, and list-to-net distortions (2019–2024).